







Non-surgical management of hallux valgus can be multifaceted
Here is a common scenario in my practice: a patient arrives with bunion pain, imaging in hand, already resigned to the operating room. The angle looks severe. The joint appears arthritic. The assumption—shared by many patients and even some clinicians—is that structural deformity on imaging predicts symptoms and dictates treatment.
It does not always work that way.
Imaging findings in hallux valgus do not consistently correlate with pain or functional limitation. I have seen patients with dramatic deformities walk comfortably, and others with modest changes struggle with daily activity. The bunion is not just a bone problem. It is a biomechanical, soft-tissue, and often pain-processing problem. That distinction matters because it opens the door to treatments that do not involve osteotomy, screws, or months of recovery.
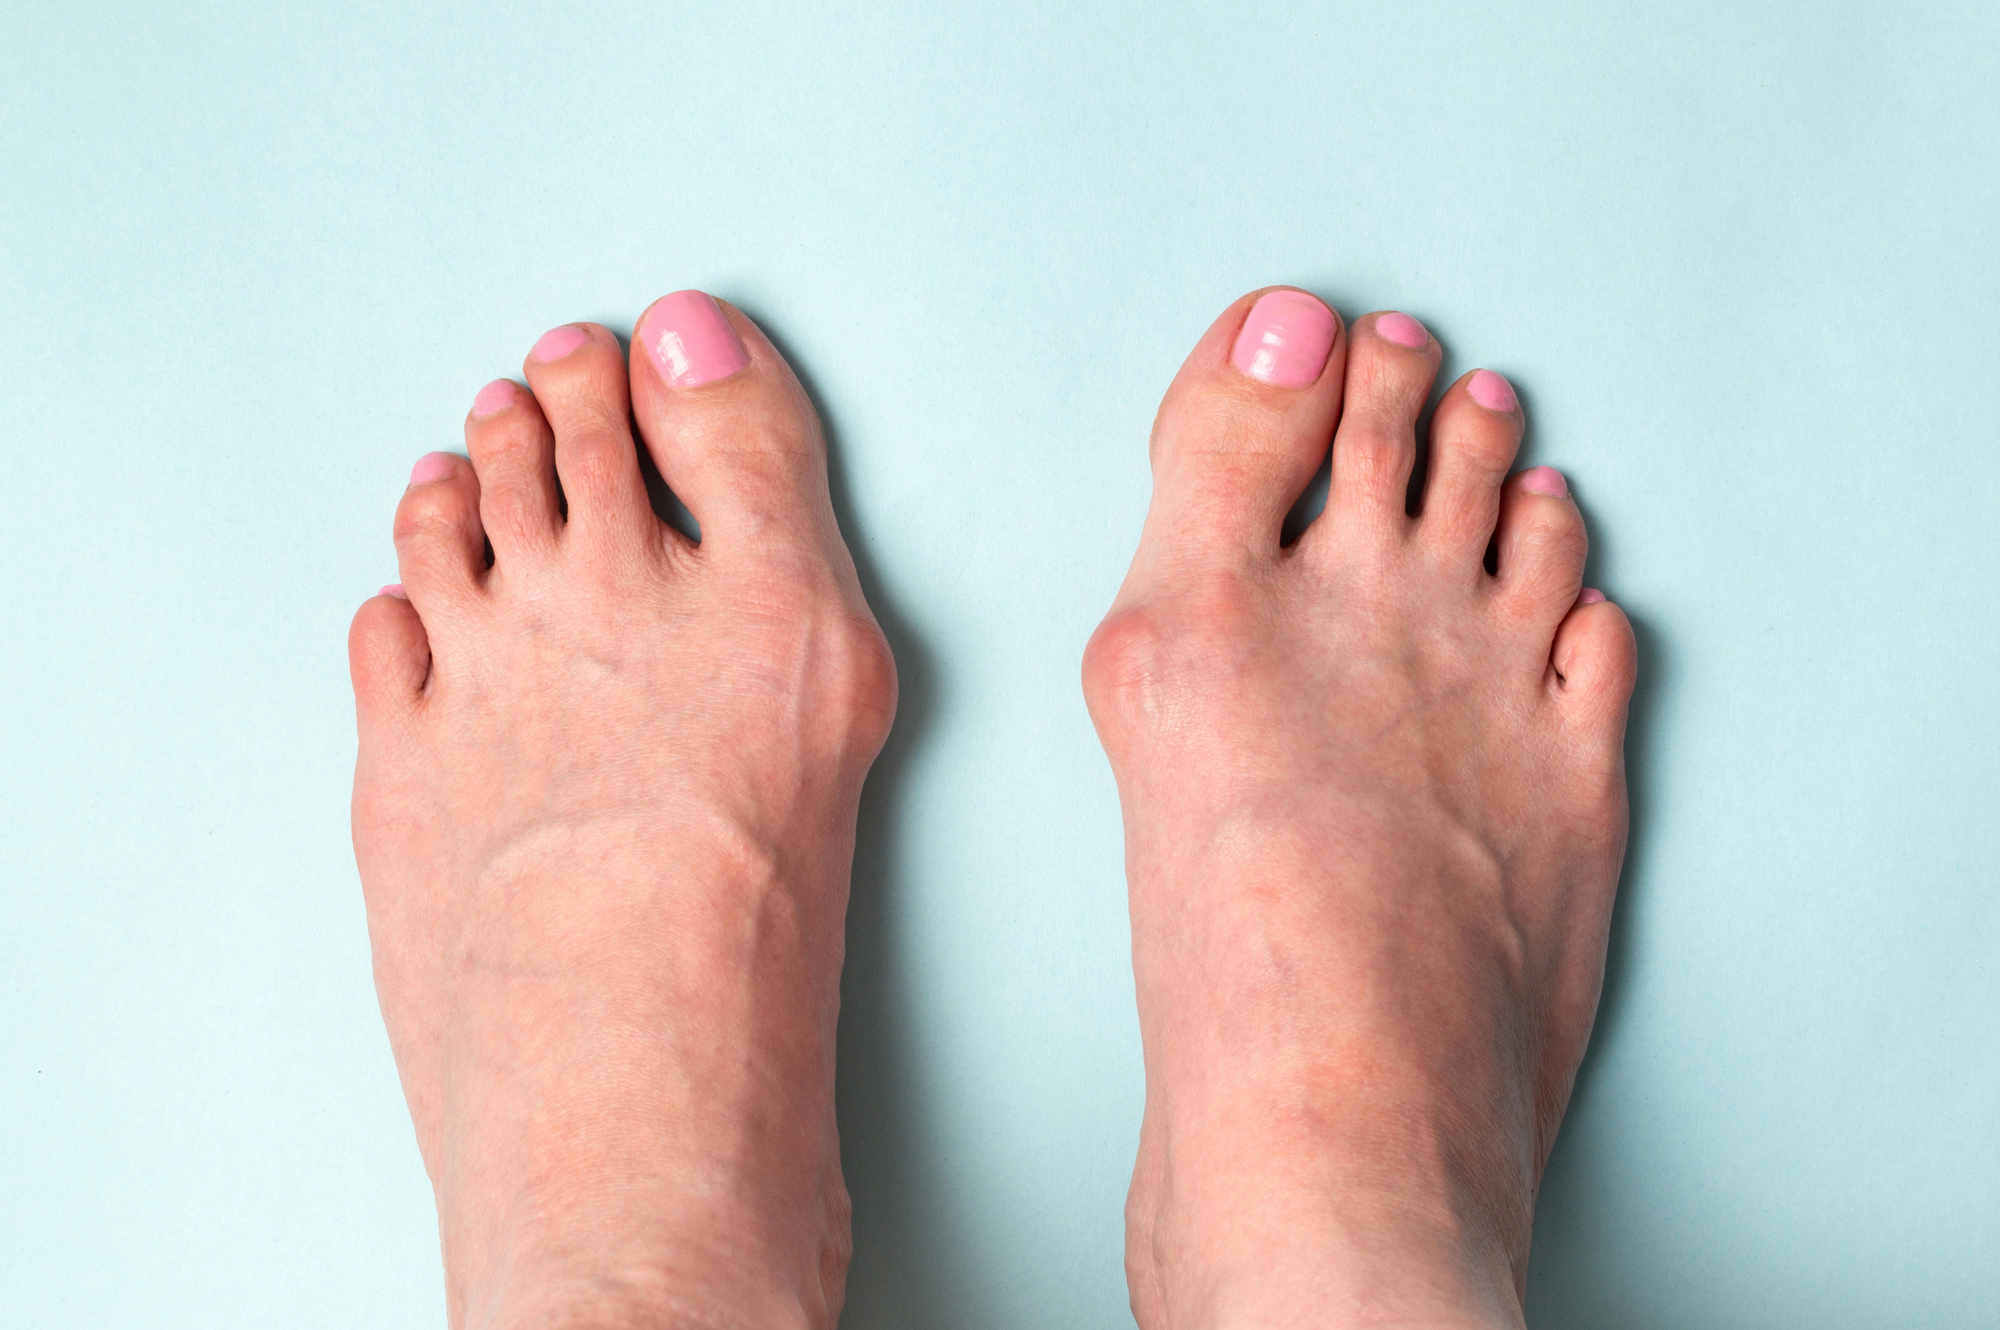
bunions ()The studies you may have encountered from 2022 established an important baseline: non-surgical management of hallux valgus can be multifaceted, but evidence for individual interventions remains limited. Researchers at the time noted that footwear modification, foot orthoses, and exercises showed preliminary promise, yet these approaches had rarely been studied in combination. (1)
Since then, the conversation has shifted. Regenerative medicine—therapies that harness the body’s own repair mechanisms rather than replacing or cutting tissue—has moved from experimental footnote to clinically relevant option. The question is no longer “Can we avoid surgery?” but rather “What biological tools can we use to address pain, function, and joint health before surgical intervention becomes necessary?”
Platelet-Rich Plasma (PRP)
PRP has become one of the more widely studied biologic interventions for foot and ankle conditions. The rationale is straightforward: platelets contain growth factors that modulate inflammation and promote tissue repair. In the context of hallux valgus, PRP is typically injected into the first metatarsophalangeal (MTP) joint and surrounding soft tissues.
Recent literature supports what many clinicians have observed anecdotally. PRP injections can provide meaningful pain relief and functional improvement, particularly in patients with early to moderate degenerative changes. A 2024 prospective cohort study on knee osteoarthritis—relevant because the MTP joint behaves similarly in many respects—demonstrated that PRP not only provides early pain relief but sustains it over six months, with the most pronounced improvement seen at the 24-week mark. (2) The mechanism appears to be primarily anti-inflammatory and pain-modulating rather than immediate structural regeneration. (3)
For hallux valgus specifically, PRP is increasingly viewed as a chronic pain management strategy that may also support ligament and soft-tissue integrity around the deformed joint. It is safe, autologous, and cost-effective relative to surgical alternatives. That said, PRP does not correct bony deformity. It addresses the biological environment around it.
Prolotherapy
Prolotherapy—typically dextrose-based injections targeting ligaments and joint capsules—has gained traction as a conservative option for joint instability and pain. The mechanism involves creating a controlled inflammatory response that stimulates tissue repair.
A 2023 randomized trial comparing dextrose prolotherapy to corticosteroid injection for knee osteoarthritis found that while corticosteroids provided faster short-term pain relief, prolotherapy’s effects were more durable. By three months, the prolotherapy group demonstrated superior pain reduction and functional improvement. (4) For hallux valgus, where ligamentous laxity and joint instability often contribute to pain and progression, this sustained effect is clinically relevant.
The implication: patients seeking alternatives to repeated corticosteroid injections—which can degrade cartilage over time—may find prolotherapy a reasonable middle ground. It does not reverse deformity, but it can reduce pain and improve joint stability in many cases.
Stem Cell Therapy
Mesenchymal stem cells (MSCs)—derived from bone marrow, adipose tissue, or placental sources—represent the most ambitious frontier in regenerative foot and ankle care. These cells can differentiate into bone, cartilage, and tendon cells, offering theoretical potential for structural repair.
A 2021 case report documented improvement in symptoms and function following adipose-derived MSC injection into a first MTP joint with osteoarthritis, with benefits sustained at nine months. (5) More recent reviews, including a 2025 Frontiers in Bioengineering and Biotechnology analysis, confirm that stem cells enhance functional recovery in ankle osteoarthritis and show promise in cartilage repair contexts. (6)
Stem cell therapy for hallux valgus remains investigational.
Hyaluronic Acid
Hyaluronic acid injections, familiar to many knee osteoarthritis patients, have been studied in hallux rigidus and MTP joint degeneration. A 2025 systematic review found that intra-articular injections—including hyaluronic acid—provided effective pain relief and improved range of motion in early-stage osteoarthritis, though benefits typically lasted less than 12 months. Approximately half of patients required surgical intervention within a year. (7)
For hallux valgus with associated joint degeneration, hyaluronic acid may offer temporary symptomatic relief. It is not a disease-modifying therapy, but it can be a useful bridge for patients who are not yet ready for surgery or who wish to trial conservative measures.
Non-Surgical Management
The most effective conservative approach to hallux valgus is rarely a single intervention. In my practice, I typically recommend a structured, multimodal protocol:
- Biomechanical optimization: Custom or semi-custom orthoses that redistribute pressure away from the medial eminence and support the medial longitudinal arch.
- Footwear modification: Shoes with a wide toe box, low heel, and adequate depth. This is not a cosmetic preference—it directly alters joint loading.
- Targeted strengthening: Progressive resistance exercises for the intrinsic foot muscles, particularly hallux plantarflexion. A 2023 trial demonstrated approximately 20% improvement in hallux strength over 12 weeks, which may help stabilize the joint dynamically. (8)
- Regenerative injection therapy: PRP or prolotherapy for patients with persistent pain despite biomechanical measures, particularly those with early degenerative changes or soft-tissue irritation.
- Activity modification and load management: Temporary reduction in high-impact activities that exacerbate symptoms, with gradual reintroduction as tolerance improves.
This approach does not promise to straighten the toe. It aims to reduce pain, preserve function, and delay—or sometimes avoid—surgical intervention.
When Surgery Remains the Right Choice
I want to be clear: regenerative medicine is not anti-surgery. It is pro-appropriate-timing. Surgical correction—whether through minimally invasive chevron and Akin osteotomies (MICA), scarf osteotomy, or Lapidus procedures—remains the definitive treatment for severe deformity, progressive joint destruction, or failure of well-executed conservative care.
The 2022 MICA study of 106 feet demonstrated that third-generation minimally invasive surgery can achieve substantial deformity correction with significant clinical improvement at two years. (9) For patients with severe hallux valgus, this is valuable data.
However, the same body of research reminds us that surgical outcomes are not purely technical. Patient satisfaction is moderated by psychosocial factors, expectations, and the ability to return to normal life. Women in particular have reported that footwear and clothing limitations post-surgery negatively impact self-esteem—a reminder that forefoot conditions are multifaceted and that recovery extends beyond radiographic alignment. (10)
The bunion you see on X-ray is not always the bunion that hurts
If there is one principle I hope patients and clinicians take from this update, it is this: the bunion you see on X-ray is not always the bunion that hurts.
Imaging provides structural information. It does not reliably predict symptoms, guide prognosis, or dictate treatment in isolation. A patient with moderate deformity and significant soft-tissue inflammation may benefit from PRP and physical therapy. A patient with severe deformity but minimal pain may simply need footwear modification and observation. Conversely, a patient with modest radiographic changes but relentless pain and functional limitation may be the best candidate for surgical consultation.
Careful clinical evaluation—assessing pain patterns, joint stability, activity demands, and patient goals—matters more than any single image.
Summary
Hallux valgus treatment in 2026 is not about choosing between “conservative” and “surgical.” It is about understanding what each approach can and cannot do, and sequencing interventions thoughtfully.
Regenerative medicine offers genuine promise: PRP for pain modulation and tissue support, prolotherapy for ligamentous stability, and stem cell therapy as an evolving option for joint health. None of these reverse structural deformity. All of them can improve biological environment, reduce symptoms, and extend the window during which surgery remains elective rather than urgent.
The most sophisticated treatment plan is not the one that uses the newest technology. It is the one that matches the right intervention to the right patient at the right time—and recognizes that the patient in front of you is more complex than any radiograph can capture.
References
- Menz HB, Lim PQ, Hurn SE, Mickle KJ, Buldt AK, Cotchett MP, Roddy E, Wluka AE, Erbas B, Munteanu SE. Footwear, foot orthoses and strengthening exercises for the non-surgical management of hallux valgus: protocol for a randomised pilot and feasibility trial. Journal of Foot and Ankle Research. 2022 Dec;15(1):1-0.
- Murugesan T, et al. Clinical and Functional Outcomes Following Intra-articular Platelet-Rich Plasma Injection for Knee Osteoarthritis: A Prospective Cohort Study. Cureus. 2024 Oct 25.
- Husain A, et al. From Platelet Rich Plasma to Mesenchymal Stem Cells: Cartilage, Tendon, and Bone Regeneration with Orthobiologics. Instructional Course Lectures. 2024;73:3-13.
- Bayat M, et al. Comparison of Dextrose Prolotherapy and Triamcinolone Intraarticular Injection on Pain and Function in Patients with Knee Osteoarthritis: A Randomized Clinical Trial. Archives of Bone and Joint Surgery. 2023.
- Braile A, et al. Hallux rigidus treated with adipose-derived mesenchymal stem cells: A case report. World Journal of Orthopedics. 2021;12:51-5.
- Yang L, et al. Applications of bone regenerative medicine in the foot and ankle: mechanisms, technologies, and therapeutic advances. Frontiers in Bioengineering and Biotechnology. 2025.
- Monestier L, et al. Hallux rigidus: are only injections worth it?—a systematic review. AME Surgical Journal. 2025.
- Menz HB, et al. Nonsurgical management of hallux valgus: findings of a randomised pilot and feasibility trial. Journal of Foot and Ankle Research. 2023.
- Lewis TL, Ray R, Gordon DJ. Minimally invasive surgery for severe hallux valgus in 106 feet. Foot and Ankle Surgery. 2022 Jan 31.
- Dismore LL, van Wersch A, Critchley R, Murty A, Swainston K. A qualitative study to understand patients’ experiences of their post-operative outcomes following forefoot surgery. British Journal of Pain. 2022 Jun:20494637211060278.